What Is Insulin Resistance? 7 Early Signs to Watch For
September 22, 2026
Insulin resistance happens when your body's cells stop responding normally to insulin, the hormone your pancreas releases to move sugar out of the bloodstream and into cells for energy. Normally, insulin acts like a key that unlocks cells so glucose can enter and get used for fuel. When cells become resistant, that key stops working as well, and glucose has a harder time getting where it needs to go.
Your pancreas responds to this resistance the only way it knows how: by producing more insulin to try to force the same effect. This compensation, called hyperinsulinemia, can mask the underlying problem for years, since blood sugar can stay in a normal range even as insulin resistance quietly develops underneath. Blood sugar itself typically doesn't become abnormal until the pancreas can no longer keep up with the increased demand, which is often the point at which prediabetes or type 2 diabetes gets diagnosed. By then, insulin resistance has usually been building silently for years.
How Common Is Insulin Resistance?
Insulin resistance is far more widespread than most people realize, in large part because it usually causes no obvious symptoms until it has progressed significantly. A widely cited analysis of national health survey data found that roughly 40% of U.S. adults aged 18 to 44 show measurable insulin resistance based on standard lab-based testing, even though very few of them have been diagnosed with it directly.
Longer-term tracking of the same national survey data shows this trend moving in the wrong direction. Between 1999 and 2018, the measured prevalence of insulin resistance among adults without diabetes rose from roughly 25% to over 38%, with the increase showing up across virtually every demographic group. Researchers have linked part of this rise to increasing rates of obesity, but rising rates of high blood pressure, unfavorable cholesterol patterns, and reduced physical activity have all contributed as well, independent of body weight alone.
What Causes Insulin Resistance?
Several overlapping factors can drive insulin resistance, and most people who develop it have more than one at play simultaneously. Excess body fat, particularly visceral fat around the abdomen and organs, is the single strongest driver, since this type of fat tissue releases inflammatory signals that directly interfere with insulin's ability to communicate with cells.
Physical inactivity compounds the problem in a very direct way: muscle is one of the largest consumers of blood glucose in the body, and muscles that aren't regularly used become less responsive to insulin's signal over time. Genetics also plays a real role, since having a parent or sibling with type 2 diabetes meaningfully raises your own risk of insulin resistance, independent of lifestyle factors.
Poor sleep and chronic stress both elevate cortisol and other stress hormones that work against insulin's normal function, which is part of why insulin resistance is more common in people with long-term sleep deprivation or ongoing high-stress circumstances. Certain medications, including some steroids, and hormonal conditions like polycystic ovary syndrome, can also contribute, as can simply getting older, since insulin sensitivity tends to decline somewhat with age even independent of other factors.
How Is Insulin Resistance Diagnosed?
There is no single blood test result that definitively confirms insulin resistance the way a pregnancy test gives a yes-or-no answer. The most precise research method, called the hyperinsulinemic-euglycemic clamp, is accurate but impractical for routine clinical use, since it requires hours of continuous IV monitoring.
In everyday practice, providers typically rely on a calculation called HOMA-IR, which combines a fasting blood glucose level with a fasting insulin level to estimate how hard your pancreas is working to keep blood sugar normal. A fasting glucose test, an A1C, which reflects average blood sugar over roughly three months, and sometimes an oral glucose tolerance test round out the typical workup, especially when other signs on this list are present.
Can Insulin Resistance Be Reversed?
In many cases, yes, especially when it's caught before it progresses to type 2 diabetes. Lifestyle changes are considered the foundation of treatment, and they work because they address the root mechanisms rather than just the downstream blood sugar numbers.
Exercise is particularly effective because muscle contraction itself triggers glucose uptake through a pathway that doesn't require insulin at all, meaning physical activity can improve blood sugar control even before any weight is lost. Even modest weight loss, in the range of 5 to 7% of body weight, has been shown to meaningfully improve insulin sensitivity in people who are overweight, since reducing visceral fat directly reduces the inflammatory signals driving the resistance in the first place.
Improving sleep quality and duration, reducing chronic stress, and adjusting diet, particularly reducing refined carbohydrates and added sugars, all support the same underlying goal. In some cases, particularly for people already diagnosed with prediabetes, a provider may also recommend medication such as metformin alongside lifestyle changes to help improve insulin sensitivity.
7 Early Signs to Watch For
Here are seven signs that can show up before insulin resistance progresses to a diabetes diagnosis.
1. Weight Gain, Especially Around the Abdomen
Insulin resistance and abdominal weight gain often reinforce each other in both directions. Excess visceral fat, the fat surrounding abdominal organs as opposed to fat under the skin, releases inflammatory compounds that directly interfere with insulin's ability to signal cells effectively.
At the same time, high insulin levels themselves promote fat storage, particularly in the abdominal area, since insulin is fundamentally a storage hormone. This creates a cycle where insulin resistance encourages more abdominal fat, and more abdominal fat worsens insulin resistance.
2. Fatigue After Meals
When cells resist insulin's signal, glucose has a harder time actually entering cells to be used for energy, even though blood sugar levels may be elevated. The result can feel counterintuitive: plenty of sugar is present in the blood, but the body's cells are functionally starved of usable fuel.
This mismatch is part of why some people feel unusually sleepy or sluggish specifically after carbohydrate-heavy meals, rather than energized by the food they just ate.
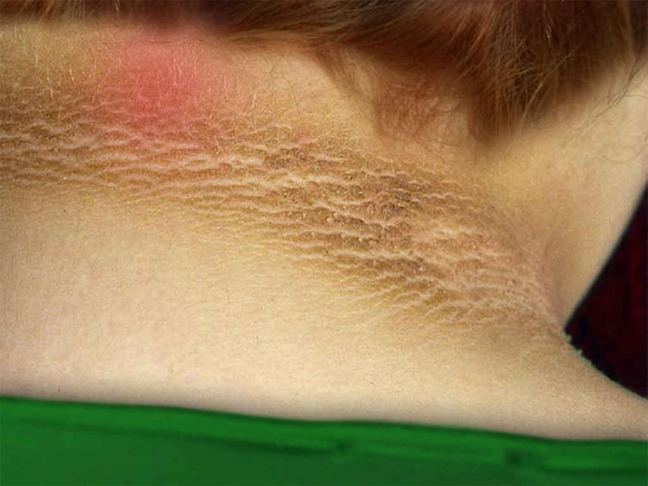
Dark, velvety patches of skin, often at the neck, armpits, or groin, are one of the more visible physical signs of significant insulin resistance. High circulating insulin levels can stimulate skin cells to multiply and produce excess pigment in these areas.
This particular sign is notable because it's something a person or a provider can actually observe directly, unlike most of the internal metabolic changes on this list, making it a useful visual cue during a physical exam.
4. Sugar and Carb Cravings
Since cells aren't efficiently taking in the glucose already available in the bloodstream, the brain can continue signaling hunger and a craving for quick energy sources, even shortly after eating. This isn't a willpower issue; it reflects a genuine mismatch between the fuel available in the blood and the fuel cells can actually access.
Frequent cravings for sugary or refined carbohydrate foods, especially soon after a meal, can be one signal worth mentioning to a provider alongside other symptoms.
5. Difficulty Losing Weight Despite Effort
Because high insulin levels promote fat storage and make it harder for the body to access stored fat for energy, insulin resistance can make weight loss efforts feel disproportionately difficult compared to someone without it, even with similar diet and exercise changes.
This is one of the more frustrating aspects of insulin resistance for many people, since it can create the impression that something isn't working, when the underlying hormonal environment is actively working against the effort.
6. High Blood Pressure
Insulin resistance and high blood pressure frequently occur together, partly because high insulin levels can cause the kidneys to retain more sodium and water, and partly because insulin resistance is associated with changes in blood vessel function that make them less able to relax and widen normally.
This overlap is significant enough that insulin resistance, abdominal weight gain, high blood pressure, and abnormal cholesterol are often grouped together as metabolic syndrome, since they tend to cluster in the same individuals and share underlying causes.
7. Irregular Menstrual Cycles or PCOS
In women, insulin resistance is closely linked to polycystic ovary syndrome, or PCOS, since high insulin levels can stimulate the ovaries to produce excess androgens, or male hormones, disrupting normal ovulation and menstrual regularity.
This connection is well-established enough that insulin resistance testing is a standard part of a PCOS workup, and improving insulin sensitivity is often a core part of managing PCOS symptoms.
Why Catching This Early Matters
Because insulin resistance can be present for years before blood sugar itself becomes abnormal, catching it early through bloodwork, rather than waiting for symptoms, creates a much wider window for lifestyle changes to make a real difference before a type 2 diabetes diagnosis. Given how common insulin resistance has become, and how much of it goes undiagnosed, a simple conversation with a provider is often the only thing standing between years of silent progression and an actionable plan.
If several of these signs sound familiar, a simple blood test can check your insulin and glucose levels together. CareArc's primary care team can help you understand your results and build a plan from there. Request an appointment to get started.